Fertility Testing
Comprehensive Fertility Testing: Precision Diagnostics for Both Partners
Accurate diagnosis is the foundational cornerstone of successful fertility treatment. At Jabalpur Hospital Embryology & Laparoscopy Centre, we provide comprehensive, same-day diagnostic evaluations for both female and male partners under one roof. Our precision pathology, automated chemiluminescence hormone assays, and high-resolution ultrasound folliculometry deliver the clinical clarity required to build an effective personalized roadmap.
What Does an AMH Test Tell You?
Anti-Müllerian Hormone (AMH) directly reflects your remaining ovarian egg pool. Unlike cycle-dependent hormones, AMH remains stable throughout the menstrual month, providing reliable guidance to tailor fertility medication doses and predict stimulation response.
Optimal Baseline Hormone Testing
Testing baseline FSH, LH, and Estradiol on Day 2 or Day 3 of your menstrual cycle delivers an accurate physiological snapshot of pituitary gland coordination and ovarian follicular recruitment.
Follicular Monitoring & Ovulation Study
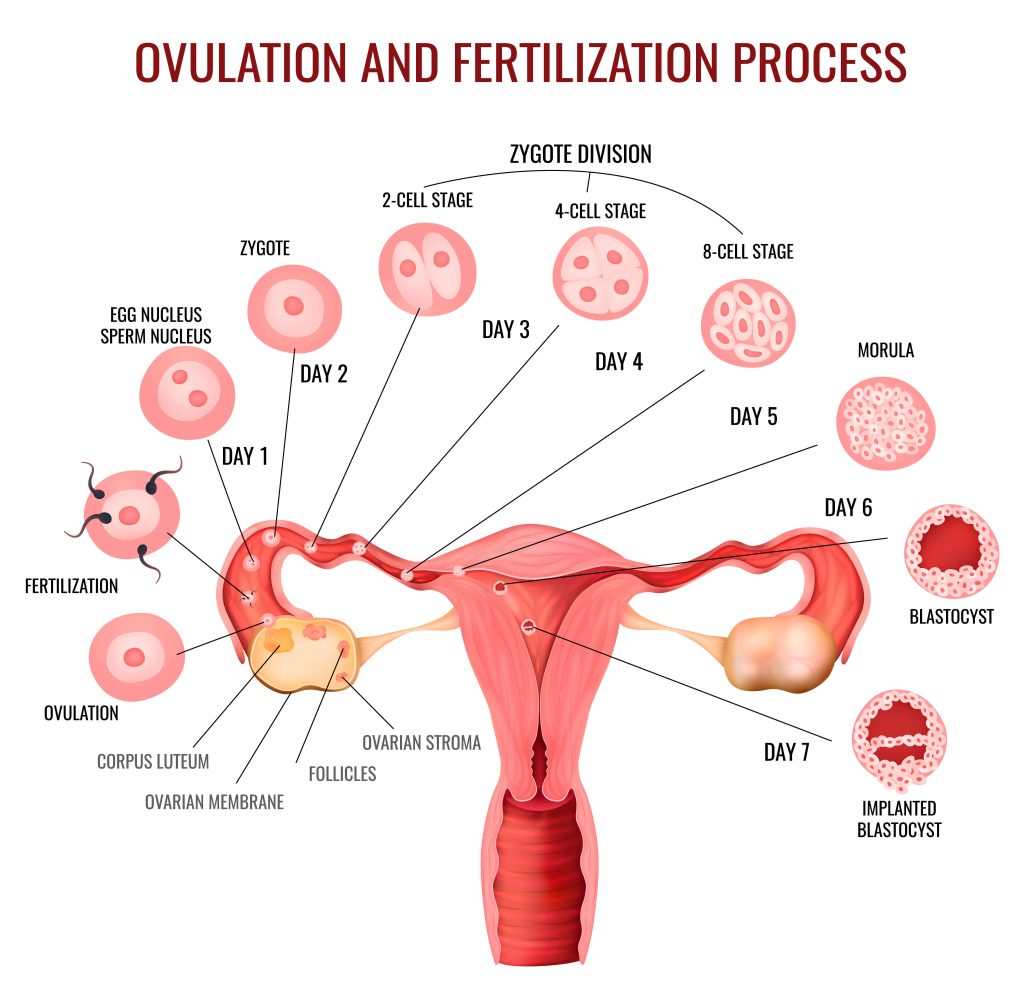
High-resolution serial transvaginal sonography tracks dominant follicle maturation, ovulation rupture, and endometrial synchronization:
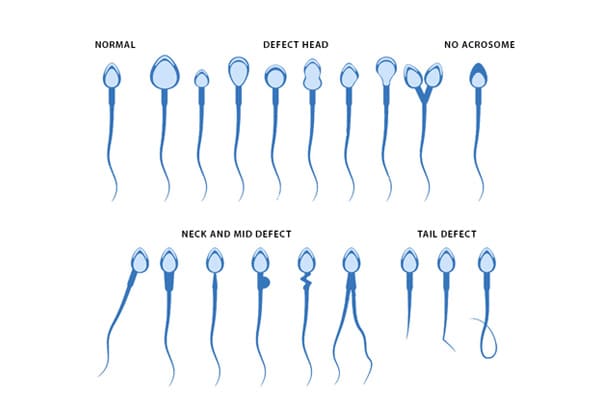
Computer-Assisted Semen Analysis (CASA) & Morphology
Evaluated in accordance with World Health Organization (WHO 6th Edition) international laboratory standards:
Complete Fertility Diagnostic Services
Our specialized diagnostic infrastructure covers all clinical facets of male and female reproductive evaluation:
24x7 In-House Pathology
Round the clock diagnostic testing for critical hormonal surges, complete blood counts, coagulation profiles, and pre-operative clearances.
Complete Hormone Profile
Automated chemiluminescence testing for AMH, FSH, LH, Estradiol, Progesterone, Prolactin, Free Testosterone, and Thyroid panels.
Andrology & Semen Analysis
Standard microscopic and computerized assessment of sperm count, viability, Kruger strict morphology, and semen fructose levels.
High-Resolution Folliculometry
Serial transvaginal color Doppler ultrasound to monitor follicular recruitment, ovulation confirmation, and uterine perfusion.
Tubal Patency Testing
Hysterosalpingography (HSG) and saline infusion sonohysterography (SIS) to confirm unblocked fallopian tubes and uterine cavity contour.
Advanced Endoscopy Unit
Fertility-enhancing diagnostic and operative laparoscopy and hysteroscopy to identify and correct endometriosis, polyps, and adhesions.
Understanding Ovarian Reserve
Ovarian reserve reflects both the quantitative pool and qualitative potential of eggs remaining within the ovaries. While age is an influential biological benchmark, individual ovarian reserves vary widely due to genetics, prior surgeries, and lifestyle factors.
High Ovarian Reserve
- Abundant Follicle Pool: High AMH (> 3.0 ng/mL) and strong Antral Follicle Count.
- Favourable Stimulation Response: Readily develops multiple mature oocytes for fertilization.
- Higher Blastocyst Selection: Surplus high-grade embryos available for cryopreservation.
- OHSS Prevention Focus: Regulated mild antagonist stimulation ensures safe cycles without hyperstimulation.
Low Ovarian Reserve (Low AMH)
- Reduced Antral Cohort: Lower AMH (< 1.0 ng/mL) and fewer resting follicles.
- DuoStim Dual Protocol: Double ovarian stimulation within one single menstrual cycle to maximize cumulative egg collection.
- Individualized Embryology: Specialized micro-incubation and ICSI micro-injection maximize blastocyst conversion from every mature egg.
- Pregnancy is Still Achievable: Low AMH reflects egg quantity, not egg quality. Tailored clinical care consistently delivers success.
Clinical Insight: Low AMH does NOT equal infertility. It indicates that fewer eggs are recruited each cycle, not that viable eggs are absent. Advanced protocol customizations such as DuoStim and physiological micro-incubation at our centre give couples with low AMH excellent odds of biological conception.
Advanced Surgical & Endoscopic Diagnostics
When imaging or hormone testing indicates structural barriers, minimally invasive endoscopic surgery provides both definitive diagnostic visualization and immediate surgical correction in the same session: